
Since 2013, a practical solution has been available in the Netherlands to help doctors and patients taper medications gradually and safely. This solution consists of so-called tapering strips: medication packaged in a sequence of daily doses that allows patients to reduce their dosage in very small steps over a period of weeks, months, or, if necessary, years. The key innovation is simple. Tapering strips contain lower and intermediate dosages than those made commercially available by pharmaceutical companies. These dosages were specially made by the Dutch Regenboog Pharmacy at the request of patients who were unable to discontinue their medication safely using only standard dosage forms.
The use of tapering strips allows doctors and patients to design a gradual, individualized, and potentially hyperbolic tapering schedule from any starting dose to any desired end dose—including zero if complete discontinuation is the goal. Once the starting dose, target dose, and duration have been determined, the pharmacy prepares all medication required for the chosen tapering trajectory. Each day’s medication is packaged in an individual sachet containing exactly the intended dose. No tablet splitting, capsule opening, bead counting, liquid manipulation, tablet shaving, weighing of tiny quantities, or complicated calculations are required. Tapering becomes a simple daily routine rather than a technically demanding, time-consuming and error-prone exercise.

It was clear from the very beginning that tapering strips would make safe and responsible tapering much easier for both doctors and patients, and that reimbursing them would be a rational and sensible policy choice. Most Dutch health insurers, however, have taken a different view. They consider it more economical, from their own perspective, to have patients taper using only commercially available dosage forms than to reimburse tapering medication packaged in tapering strips.
Recently, two Dutch economists conducted an economic analysis that examined not only the direct costs of reimbursing tapering strips, but also the longer-term benefits and the effects in other societal domains. Their conclusion is striking. They conclude that full reimbursement of tapering strips is not only economically rational, but would also generate substantial structural savings for the Dutch government. For antidepressants alone, they estimate that full reimbursement of tapering medication could result in annual savings of between €2 and €4 billion.
In their economic analysis, different forms of market failure explain why a policy that would benefit patients, healthcare professionals, health insurers, and society as a whole has nevertheless failed to be implemented thus far.
Market Failure I: The Pharmaceutical Industry Failed to Supply What Was Needed
For decades it has been known that many psychiatric—and other—medications can cause serious withdrawal problems when they are stopped too abruptly. What many people still do not realize is that, until recently, doctors had very limited practical means to help patients avoid these problems. The reason was straightforward: the lower and intermediate dosages required for gradual tapering were simply not available. Pharmaceutical companies had developed and marketed medications intended for treatment, but not the dosage forms required for discontinuation. As a result, doctors often had no choice but to reduce doses in steps that were larger than many patients could comfortably tolerate. The consequences of this omission have been substantial. Millions of patients worldwide have been exposed to avoidable withdrawal problems because the dosage forms required for safe discontinuation were not made available.
Evidence That Tapering Strips Are Effective Is Available
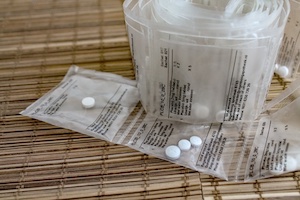
Since 2013, increasing numbers of Dutch patients have used tapering strips. This has allowed me and Jim van Os to conduct observational studies involving more than 2,800 participants. These studies have shown that the use of tapering strips is safe and highly effective: approximately 70% of participants—including many who had previously failed one or more attempts to discontinue medication—were able to taper successfully. Preliminary data we have suggest that these outcomes are likely to improve further, when tapering trajectories are made longer and more consistently hyperbolic throughout the entire process. In short, the Netherlands now has a practical solution that allows medications such as antidepressants, benzodiazepines, antipsychotics, opioid painkillers, and anti-epileptic drugs to be discontinued much more gradually and safely than was previously possible.
Market Failure II: The Reimbursement System rewards short-term thinking
Given the availability of a practical solution and the growing evidence supporting its use, one might expect tapering strips to be welcomed by health insurers. Initially, this was indeed the case. When tapering strips were introduced in 2013, the lower dosages they contained were reimbursed by all Dutch health insurers. This changed in 2016, when most insurers stopped reimbursing tapering medication packaged in tapering strips. Their reasoning appeared simple: reimbursement of tapering strips was considered more expensive than asking patients to taper using only commercially available dosage forms. The focus was on costs incurred by the insurer itself. What this meant for patients, their doctors, and society as a whole appeared to receive much less attention. This represents a market failure: decisions were based on short-term expenditures within one part of the healthcare system, rather than on total societal costs and benefits.
Market Failure III: The Failure of Health Technology Assessment
One might expect that such broader costs and benefits would be evaluated by the Dutch National Health Care Institute (www.zorginstituutnederland.nl), whose task it is to do this. In practice, this never happened. Formal economic evaluations are legally required only for very expensive new medicines, such as innovative cancer treatments costing hundreds of thousands of euros per patient. Tapering strips are far too inexpensive to trigger such a process. Paradoxically, this means that a relatively inexpensive intervention capable of affecting very large numbers of patients escaped the type of comprehensive assessment that would normally consider both costs and benefits. As a result, the central question—whether reimbursement of tapering strips is economically rational from a societal perspective—remained unanswered for almost a decade.
The Missing Economic Calculation
That situation has now changed. Two Dutch economists, one of whom works at the Netherlands Bureau for Economic Policy Analysis (CPB), recently conducted an economic analysis that considered both the costs and the benefits of reimbursing tapering medication. Their conclusion is striking. Full reimbursement of tapering medication for antidepressants is expected not only to benefit patients, but also to generate substantial savings for Dutch society.
Importantly, they point out that these savings do not primarily accrue to health insurers. Instead, they arise in other parts of government and society. One example is the justice and public safety sector, which has to deal with people experiencing severe psychological or behavioral crises. Such crises can sometimes occur when patients are forced to stop medications abruptly or are forced to taper them too quickly when lower dosages needed to taper safely are not available. To the extent that such crises are related to unsuccessful discontinuation, they may be preventable by offering patients the opportunity to taper gradually and safely.
Another example is the social security system. Difficulties arising from unsuccessful attempts to discontinue medication can contribute to prolonged sickness absence, loss of employment, and dependency on social benefits. Here too, enabling patients to taper gradually and safely may help prevent avoidable social and economic costs.
The central insight of the economists’ analysis is therefore that the costs of reimbursement are borne largely by health insurers, whereas many of the benefits accrue elsewhere in society. When these broader societal benefits are taken into account, reimbursement of tapering medication appears not only medically sensible, but also economically rational.
Based on the assumptions used in their model, the economists estimate that reimbursing tapering strips for antidepressants alone could generate annual societal savings of between €2 and €4 billion. If these estimates are correct, the Netherlands has spent years debating the costs of reimbursing tapering strips while overlooking the much larger costs associated with not reimbursing them.
Looking Beyond the Netherlands
Although this analysis was conducted for the Dutch situation, its implications extend beyond the Netherlands. Many countries face the same challenge: large numbers of patients wish to discontinue psychiatric and other medications safely, while healthcare systems lack appropriate mechanisms to support them. I therefore hope that health economists and policymakers in countries such as the United Kingdom and the United States will start to undertake similar economic analyses using their own epidemiological data, healthcare structures, reimbursement systems, and regulatory frameworks.
Conclusion
The story of the tapering strips illustrates interconnected market failures. First, pharmaceutical companies failed to supply the dosage forms required for safe discontinuation. Second, health insurers focused on short-term costs while neglecting broader societal benefits. Third, healthcare assessment systems failed to evaluate a low-cost intervention that has the potential to generate substantial long-term savings. The result is that governments may be spending billions more on psychopharmaceuticals than necessary—not because safe discontinuation is impossible, but because the systems responsible for facilitating it have thus far failed to recognize its value.
My hope is that economic analyses such as this one will help policymakers recognize that reimbursing tapering strips is not only beneficial for patients, but also economically rational. Tapering strips are available not only in the Netherlands but can also be supplied to patients in many other countries. Wider reimbursement of this form of tapering medication could therefore help reduce healthcare costs, generate substantial societal savings, and prevent a great deal of avoidable suffering among patients who wish to discontinue their medication safely.
The English translation of the economic analysis by Jessika Kersting and Jan-Maarten van Sonsbeek, entitled “Triple Market Failure: Why the Dutch Government Structurally Overpays for Psychopharmaceuticals” is available on Me Judice, a discussion platform for economists, and can be accessed here.













Even in India we need tapering strips to safely deprescribe or taper down medications
Report comment
Predetermined trajectory is not an individualised approach to the withdrawal and ceasing of psych and other related drugs. It is creating a known outcome out of an unknown situation. It’s a false positive if it works for some and not for others.
How does this medical prediction model actually work?
For all those who have not been able to taper by other means because the intended incremental decreases weren’t predictable, how then will the tapering strips be more safe?
Who will supervise the tapering off process?
How so that economic projections want to save billions in further costs, but do not address the root causes of the billions spent that led to the difficulties for stopping, ceasing, withdrawal from the said prescribed drugs?
“The use of tapering strips allows doctors and patients to design a gradual, individualized, and potentially hyperbolic tapering schedule from any starting dose to any desired end dose—including zero if complete discontinuation is the goal. Once the starting dose, target dose, and duration have been determined, the pharmacy prepares all medication required for the chosen tapering trajectory.”
Report comment
I wish and hope all those brutally overdosed by abusive punitive psychiatrists in malice hatred are allowed to taper off and quit antipsychotics all around the world that were never mentally ill tyranized by despots without due process or burden of proof or redress in court of law or cross examining ones accusers in court of law or the so called evidence of their mental malfunction in this fallen world of discrimination prejudice and jealousy etc 7 deadly sins to exact your vengeance vindictiveness in forced treatment flooding market with unwanted forced treatment in ” hire and assassin and hire a torturer lier cheat character assassination and rapist against impoverished victims nontherapeutic torture….vive la difference and freedom of thought where not danger to others proved to benefit of the law in a reputable court of law freedom.of thought freedom of perceptions and screw your mental hygiene theories discrimination to circumcise Renaissance ; the dignity of the human mind..Einstein stated the last frontier– the human mind the last battle for the soul of mankind.
Report comment
I’ve been wondering why tapering strips are not more widely available – as always, follow the money … sadly.
Report comment
Tapering strips are shipped worldwide; except those for benzodiazepines, Z-drugs and opioïds due to import restrictions.
http://www.taperingstrip.com
Report comment
People treated properly and appropriately for their distress in their current real time could also save billions – people and money.
But then how would all those prescribing experts create their self-priorities and personal wealth?
How so that asking for help, is treated with drugs, no follow-up until more drugs are prescribed, which does not equate to a true medical follow-up.
Tapering strips are not individualised, so what are the anticipated risks?
Report comment
These are valid concerns, but tapering strips are made to measure and adjustments can always be made.
Adjustment is something crucial (not only for tapering strips, but for all tapering methods) and I regret that this is not mentioned in the article.
For patients abroad, there may be practical obstacles; naturally, you do not want to continue with a dose that is causing you symptoms. That is why additional minimal doses can be supplied to allow you to adjust that dose whilst waiting for a new strip.
It would be better if lower doses were manufactured in every country. But I’m afraid that investments running into millions won’t exactly spark much enthusiasm among pharmacists.
Report comment