
In a new article published in the Journal of Addictive Disorders and Mental Health, Jose Luis Turabian, a professor of medicine at Complutense University in Spain, explores the biological changes that accompany the use of psychotropic drugs. According to Turabian, the concentration on biomedical approaches and interventions in mental health have led to psychotropic drugs being used too soon, too often, and too long.
He points out that these drugs alter our neurobiology, causing sometimes permanent and irreversible changes. He argues that these changes can turn what may have been transient symptoms into chronic, and in some cases, lifelong, mental illness. By using psychotropics to treat symptoms and alleviate acute short-term suffering, practitioners may be paradoxically increasing the duration of suffering.
“The biologistic tendency of medicine, and also of psychiatry, brings with it an increasingly early, more intense, longer-term use in mild clinical conditions and in mental health situations reactive to contexts of daily life (personal problems, couple, family, work, socioeconomic, etc.) of psychotropic drugs,” Turabian writes.
“However, practical experience in general medicine indicates that psychotropic drugs cause permanent biological changes that can structure and chronify mental illnesses that would have evolved towards improvement without psychotropic drugs.”
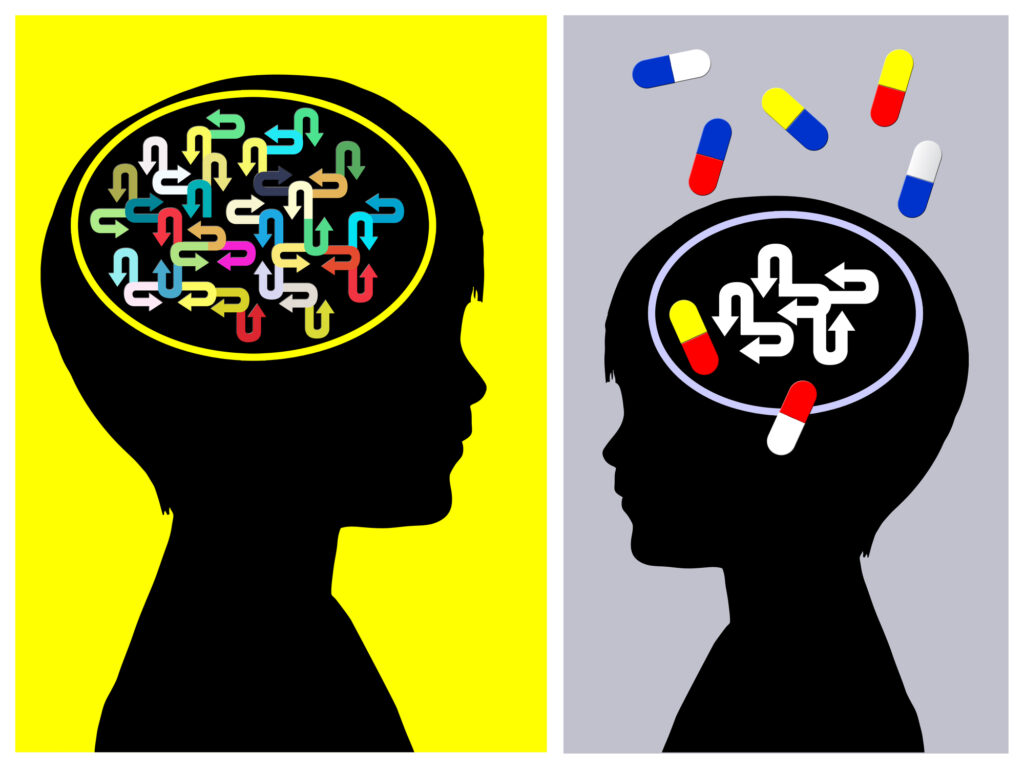 New research has questioned the efficacy of antidepressants and investigated the potential harms of long-term use. Researchers have noted that in a nine-year follow-up comparing depression patients that took antidepressants versus those that did not, antidepressants appeared to worsen long-term outcomes. This was true even when researchers controlled for depression severity. In addition to the lack of efficacy and potential for harm, antidepressants are likely overprescribed.
Recently, more attention is being paid to the difficulties of withdrawing from antidepressant medications after long-term use. In some cases, recovery from these medications can span decades, with withdrawal symptoms commonly misdiagnosed as a return of the initial mental illness. Even when these drugs work as intended, the adverse effects can be severe.
Similarly, antipsychotics have a wide range of well-documented negative long-term effects. Recent research has shown that antipsychotic use damages several areas of the brain, increases the risk of dementia, and is associated with early death. Researchers have also found that when people diagnosed with schizophrenia discontinue antipsychotic use, their cognitive functioning improves.
Turabian begins by problematizing the overmedicalization of distress by doctors. Both overdiagnosis and misdiagnosis are increasing, and so is the usage of psychotropic drugs, leading to polypharmacy — doing more harm than good. Most importantly, there is a severe shortage of research on the long-term effects of psychopharmaceuticals.
The author has conducted a review and reflected on personal experience to write about the consequences of liberally using psychopharmaceuticals in the long run, especially for issues of anxiety and depression. He specifies that the article should be considered his personal view on the issue.
The author writes that psychiatry mistakenly follows the logic behind antibiotics in calling its treatments antidepressants and antipsychotics. These names are metaphors that assume that psychiatric issues are threats that come from outside and harm the host and thus need to be removed. This metaphor has allowed the discipline to look past the numerous adverse effects of their treatments. The dangerous assumption that keeps harming patients is that what makes them feel better is also what keeps them well.
Turabian lists several reasons we should be wary of antidepressants – the effect sizes of their efficacy in clinical trials are small, long-term effects are unexamined, psychotherapies and psychosocial treatments often show similar or better outcomes without adverse effects of the drugs, and “only one in nine patients benefit from antidepressants.”
Mood disorders are often transient states caused by distressing life circumstances and would have been resolved with “watchful waiting” instead of a premature antidepressant prescription. Many of these drugs produce lasting changes in the bodies of patients. For example, benzodiazepines can lead to neurocognitive changes, and in zebrafish, early exposure to antidepressants can be seen in three generations of offspring. The author emphasizes that one of the main effects of psychotropics is suppression:
“Neuroleptics suppress motivation and imagination and interfere with the regulation of body shape and movement; Benzodiazepines suppress behavioral control and discrimination; Selective serotonin reuptake inhibitors suppress the erotic core. Suppression is essential to their effect, not a side-effect of their attack on a specific disease process.”
Often, in the case of antidepressants, the long-term effects are the opposite of the initial ones, leading to iatrogenic comorbidity. In other words, antidepressants can lead to chronic depression and increase susceptibility to depressive episodes. Similar findings have been reported for psychosis where dopamine supersensitivity can be caused by long-term use of antipsychotics, in turn leading to more florid psychosis.
Biomedical understandings of anxiety and depression can also harm patients by blocking recovery. Instead of seeing oneself as changing and responsive to the environment, these neurochemical understandings force people to see (and experience) their distress as internal and permanent. It leads them to ignore the social conditions that might be causing it. The disease model focuses on symptom removal (as is true for most medicine), and thus the patient’s internal state is often considered insignificant. The experience of anxiety or depression becomes meaningless, and they are only seen as states to be eradicated.
On the other hand, non-biological models often consider symptoms and distress to be meaningful, context-sensitive, and even useful as they can make a person re-evaluate their self, relationships, and world. This points to an essential difference in the way these two models see causality:
“The psychological model assumes that the interaction between past experience, interpersonal relationships, and current events, with the patient’s thoughts, feelings, and behaviors, lead to changes in mood and symptoms. The medical model views disease as the primary cause of symptoms and leads to changes in thoughts, feelings, and behaviors, which interact with the patient’s interpersonal relationships, current events, and past experiences.”
Thus, in focusing on symptoms removal and not meaning, drugs often render the patient passive – numbing feelings, thwarting problem-solving, hindering memory processes and concentration, and creating dependence. Consequently, they hinder the processes of psychotherapy that could have helped the patient.
Turabian concludes by noting that these drugs have numerous effects at multiple levels beyond just neurotransmitter communication. The impact on people, such as changes in thoughts, moods, feelings, behavior, etc., are often a cause of side effects such as loss of cortical gray matter. He concludes:
“Psychotropic drugs change thoughts, feelings, and behaviors that over time become structural and permanent. In this way, the general practitioner in his continuous care over time sees passive patients, unable to understand and face the causes and consequences of their situation; These patients with many years of psychopharmacological treatment continue to suffer similar levels of anxiety, but also their contextual situation has seriously deteriorated in a chronic way; they are unrecoverable patients. Current prescribing practices need to be reformulated in light of consideration of the vulnerabilities and adverse effects of treatment.”
****
Turabian, J (2021). Psychotropic Drugs Originate Permanent Biological Changes that go Against Resolution of Mental Health Problems. A View from the General Medicine. Journal of Addictive Disorders and Mental Health. (Link)












Now, did you know, there is nothing the psychiatric profession would like more than to be able to diagnose away such annoying and unbearable dissent for them.
And, as you know, the neuroleptics that make you fat are the best tools for which to accomplish that.
Now, this is interesting but, did you know, when I was a victim of this criminal racketeering scheme, it was psych docs who were assisting with the covering up a whole series of unethical medical experiments on me — which happened to involve testing of a successful cure for herpes researchers hoped to cover up so they could be bribed by drug manufacturers of herpes management drugs like valtrex.
Well, when that whole saga was going on, I was being bullied right and left for “daring to talk about the mafia” even while I was being victimized so badly in so many ways. Criminally victimized.
Doctors were acting like the Soviet Union and trying to forcibly medicate me — I did get a few involuntary injections in the emergency room at times — for daring to “talk about the mafia” or daring to tell them I was a victim of the mafia.
However, at the same time, I note I had proof. I had saved copies of several death threats from gay men they did as part of this whole saga, including a promise from this one guy named Pete who wrote me something about how “it will all be over soon” and “the mob will shut you up.” Also, police had framed me and these were obvious frame ups too.
Here is where, see, I had a right to tell other doctors that I’d been told I was being targetted by the mafia, without them instantly yelling at me to shut up and trying to go inject me with haldol. I even told them I had documentation proving it, to no avail because they were so corrupt.
Eventually, I remember suggesting to someone that, if you really need to cover up that this is the mafia that’s involved here, it’s inappropriate for you to be saying that I am crazy or psychotic. You need to then say that PETE is the one who is crazy. (And some of the others).
And I said I hoped the mafia would decide to cover it up by declaring all of these lowlifes to be the crazy ones, rather than me. As it would serve them right.
But, with regard to this Pete guy, I mentioned that he already had love handles when I met him and was ever so slightly out of shape. And something along the lines that I hope they make him take his medicine. Take his medicine. Take his medicine til he is as fat as a house.
Of course, doctors and police all simply never did that. Despite a mountain of evidence I had — I saved every single online conversation I had with ANYONE who purported to be in the mafia and started giving me a hard time — not a single one of these guys ever got declared “crazy” for talking about the mafia and medicated. However, doctors tried their best to arrange for that to happen to me, if I dared talk about it. And they were so corrupt, I was able to get it to be only temporary as they got me to change my story in a way so as to–
Well, ok, here’s the thing. Some of these incidences involved drugs. Crystal meth. Which is known to cause paranoid delusions. So, in one case, I was able to get out of the hospital by changing my story and reversing all of my accusations, pretending that it was all because I had gotten high on crystal meth, but I am all better now.
That’s how bad the doctors were.
I even remember, in one case, talking to this woman doctor or nurse who was being bad like this and corrupt. At some point, she decided to stop arguing with me regarding the fact that all the mafia stuff I was talking about was second hand information I had gotten from others. Regardless of whether it was true, I am merely quoting others and you can’t call a quotation by me of other people a “psychotic delusion.” So then she kind of decides not to argue about that and then merely tells me: “OK, but if these people are all doing that to you, that shows you have some kind of illness and you need to take this medication.”
Can you imagine saying something like that to a rape victim? “He raped you because you are mentally ill.”
Report comment
“….New research has questioned the efficacy of antidepressants and investigated the potential harms of long-term use. ..”
I was prescribed Prothiaden antidepressant in 1984 which I consumed for a number of years. Neither going on Prothiaden, being on Prothiaden, nor coming off Prothiaden made any difference to my mood.
The reason I had been prescribed Prothiaden was (I believe) not because I had been Depressed but because I had attempted suicide twice, and had a series of suicidal hospitalizations.
I suffered Chronic and Acute AKATHISIA on the drug Fluphenazine Decanoanate Depot. And I made full Recovery as a result of Weaning myself from it.
Report comment
Wow, that’s an awesome article! This guy sounds a lot like Bob Whitaker. My only objection is the use of the term “overprescription.” How can you “overprescribe” when there is no ability to determine what the “proper” amount of “prescribing” would be? But besides that, he hits on the key issues of ineffectiveness, permanent damage, long-term deterioration, and removal of personal agency. I’d love to see this guy write an article for MIA!
Report comment
It can be very hard to even talk about the problems with psychiatry without using the language which is part of the problem in the first place.
Report comment
True dat!
Report comment
Totally agree, Steve. I’ll see your “overprescription” and raise you “overdiagnosis.” I can see an argument that in some cases, taking a psychiatric drug in the short-term that numbs emotions or produces relaxation can be helpful even as we understand the drug is not curing a brain disease, has adverse effects that should be considered alongside its potential benefits, and should only be taken briefly to help a person get through an acute crisis. I’m not saying I endorse this view but I can see how it makes sense and if so that means that at least in some rare cases, prescribing can make sense. However, diagnosis is *always* bullshit in psychiatry. There is never a case where it can be reasonably said that a person truly “has” a mental disorder given that they are all invalid social constructions pretending to be real medical illnesses.
What percentage of slaves who attempted to escape and were diagnosed with drapetomania actually had the mental illness vs. did not actually have the mental illness? What percentage of people who are grieving a significant loss and are diagnosed with major depressive disorder actually have the mental illness vs. don’t have it? What percentage of people who take an “antidepressant” and experience akathisia have experienced the emergence of latent “bipolar disorder” vs. an adverse drug reaction?
I have learned much from my time here at MIA and one key takeaway is that “overdiagnosis” is an invalid word in the “mental health” context because this term relies on the demonstrably false premise that mental disorders are valid “things” that some people “have.” But don’t take my word for it, listen to eminent psychiatrist Kenneth Kendler who just said this: https://www.madinamerica.com/2021/12/kenneth-kendler-implausible-psychiatric-diagnoses-even-approximately-true/.
Report comment
“I’ll see your ‘overprescription’ and raise you ‘overdiagnosis.'” Lol.
But I do agree, “diagnosis is *always* bullshit in psychiatry. There is never a case where it can be reasonably said that a person truly ‘has’ a mental disorder given that they are all invalid social constructions pretending to be real medical illnesses.” Indeed.
https://www.wired.com/2010/12/ff-dsmv/
http://psychrights.org/2013/130429NIMHTransformingDiagnosis.htm
Thanks for the truthful article, Richard, and Professor Jose Luis Turabian. And I do agree with Steve, I’d be nice to see Dr. Turabian write an article for MiA.
Report comment
Removed for moderation.
Report comment
This line stuck out for me:
“The dangerous assumption that keeps harming patients is that what makes them feel better is also what keeps them well.”
The unstated assumption here is that doctor/prescribers are interested in making patients feel better. That is not always the case. Oftentimes it is the wish of the prescriber to control the patient. As an example I was prescribed antipsychotics for years after I received a borderline personality diagnosis after my condition deteriorated following ECT treatments, which I now wonder if the borderline diagnosis was part of a plan to silence and discredit me because the psychiatrist who referred me to the doctor who performed the ECT treatments had been drugging me for 6 years and had not kept any records. I had tried reporting him to the American Psychiatric Association, but they wouldn’t take my complaint. After that it was multiple ECT treatments that wound up disabling me, along with the borderline diagnosis.
Sometimes making the patient feel better is the furthest thing from the doctor’s mind. I was prescribed abilify, risperdal, Geodon, Seroquel, Latuda and many more from this class. I was not psychotic. I was angry and I was vocal about why I was angry. It was not about making me feel better.
If doctors and others who prescribe or force medicate had only the patient feeling better as a goal, things would not be in the complete and utter mess they are.
Report comment
I think the goal is seldom to make people feel better. I think it is to STOP people from feeling certain things, which eventually devolves into stopping people from feeling anything at all. This is the only way that anyone could look at a semi-comatose person slumped in a chair and consider it a “treatment success.”
Report comment
I agree. That is the problem with these so-called admissions by psychiatrists and other pro-psychiatry mouthpieces. They of course are not going to admit the extent of evil greed obfuscation power games etc that is what’s really going on in the entire field and what patients are subjected to. They will say things like, oh we were trying to help and of course we were 100% with good intentions so how could anyone fault us that we made a bit of a mistake in wanting our patients to only feel better? It’s absolute rubbish. They are still lying and they will continue to lie. There is no credibility for this field ever. They want to maintain credibility? Well if I was a person who had driven under the influence a dozen times resulting in all sorts of accidents and personal injuries to others I don’t think I’d be so filled with hubris as to claim that I need to make sure I maintain credibility as a driver. It’s disgusting.
Report comment
I think the goal is for the person to stop turning up and stop complaining and stop disrupting the prescribers’ peace, with long-winded distress. Prescribers – Knowing that in four to six weeks time, the person will be too subdued to even notice that they are now having to deal with adverse effects.
Drowsy – sleep hygiene. Restless – cup of tea. Faint – drink more water. Blurred vision – referral to opthamologist. Aches and pains – go volunteer, get a life, be useful, get out of your head. Jittery – go do yoga. Migraine – neurologist. Hormonal changes – endocrinologist. Palpitations – cardiologist. Stiff muscles – get up and move, exercise. Dry mouth – suck on lollies. Constipation – eat more fibre. Can’t pee – can’t poo – can’t think – can’t stand – can’t sit – can’t write – can’t walk – … .
Don’t take these drugs in the first place.
Don’t.
If a family cannot be bothered to take time off to look after their child (any age) during a crisis, and the person is left with the pseudo carer GP, psychologist, psychiatrist, practitioner authorised to hand out drugs, keep looking for alternative non-drug supports.
Easier said than done when the job puts food on the table and keeps the roof over the head.
We should all be so fortunate as to have a supportive family, along with the necessary resources of finances and ongoing willingness.
People are leaving their families behind, alienating, estranged, great distances, and are expecting their new chosen paths to not have any stumbles and or hurdles.
Those who marry well, partner well, (reciprocal, caring), do okay.
The bottom line and end game in psychiatry and the associated prescribers and the given drugs and treatments is money. Do any of these Regulated authorities actually care about what they are doing to others? No. The governments’ people, pharma people, Health, Education, Research, have prescribers’ backs.
Crisis. They create the crisis.
Report comment
Zebrafish! Humans are now reduced to zebrafish! As far as “overdiagnosis” it’s not “overdiagnosis” it’s “false diagnosis.” It’s giving a diagnosis when there is not one needed and present. It is a similar thing for “overprescribing.” It’s “faslse prescribing.” It’s giving drugs for which there is no basis to prescribe drugs. It is a delusional fantasy that resides only in the heads of the psychiatrists and their minions. The main thing about the drugs is that they do make you into a zombie. They honestly make you dead on the inside and you walk around with a tombstone face. Your pupils enlarge, just like the illegal drugs our parents would worry that we were taking. Our noses run. We drool like a rabid dog. We walk around in a slump. Sometimes we can’t even sign our name. Sometimes, we don’t even wake up. Sometimes, we go to bathroom and fall asleep in there for hours. This is a tragedy. It makes otherwise intelligent people into zombies or worse. And if you are on these drugs for years at a time, you, may like Rip Van Winkle (how appropriate) lose years and years of your life. I am sure there are prescribers who think they are helping their “customer/patients” by giving them these drugs, but like I said earlier they are sadly extremely delusional. The question may really be: “who really is sick?” Is it the patient or the psychiatrist? Well, I think the diagnosis reflects more on the psychiatrist than on the patient. I also think that if you accept that diagnosis as true for you, you give your natural authority over to the psychiatrist, a mere mortal, when your authority should be given to God or if you choose not to believe, keep to yourself. Anyway, is better than giving to the psychiatrist, because when you do, it is as if someone has “raped your very soul.” Thank you.
Report comment
There is no authentic diagnosis. There are no authentic treatments. Psychiatry has free reign to make things up, change things, re-write things, trial things, guess things, eliminate things, add things, … .
Over-prescribing might stand for symptom prescribing, cascade prescribing, and or prescribing several medications at once leaving no possibility to discern what works per se or when or why.
We should start with the refusal to drug children. What licit drug and substance and treatment does a child actually need? THINK ABOUT IT.
Remember too, that just because there is no available research, it does not mean that something does or does not exist.
It is highly likely that the original observations of bizarre behaviours (to become known as schizophrenia) were likely due to environmental poisons, toxins, topped off with the medical treatments of the day.
“Dementia praecox is a historical psychiatric term that was used to describe a chronic, deteriorating psychotic disorder beginning in youth or early adulthood, which was later renamed schizophrenia.”
Neurosis: A historical clinical diagnosis or mental disorder involving severe distress, anxiety, or obsessive thoughts that interfere with daily functioning.
Neuroticism: A normal-range personality trait describing a person’s tendency to experience negative emotions like anxiety, moodiness, or emotional instability, which does not inherently impair everyday function.
What is anxiety? Is it caused by licit substances taken as prescribed?
What is depression? Is it caused by licit substances taken as prescribed?
Are vitamins, minerals, amino acids, organ functions, (checked by an independent third party) all in order? Are excessive amounts of artificial colours, artificial flavours, artificial preservatives, highly processed foods, high energy drinks, being consumed?
Where are these results documented in the prescribers’ notes?
Flip a coin – one side lands on give psych. drugs, the other side lands on no work/no food/no transport/no utilities. IS THIS NOT GOVERNMENT AND INDUSTRY AND INSTITUTION AND PHARMA COERCIVE CONTROL, under the guise of informed consent, freedom of choice, free will, … ?
Oh, and it must not be forgotten about all the not-for-profits, charities, that provide their 1% to 4% social contributions in the way of information booths, information brochures, and the all important but makes no difference of advocacy for those who are lesser than, and who do not get to speak directly with government representatives and policy makers.
We are quibbling over semantics and language. It is pointless. The psych. (and associated others) Glossary is deliberately vague and non-committal.
Wean off these sickening, body and mind and brain altering drugs. Start where you are. Do not give them to your infants, toddlers, children, adolescents, young adults.
Crisis? Just keep talking things through. Maybe a fully supervised short (a few days) course of a calming agent such as a relevant benzo. Seek the type of help and care, that comes without a prescription pad and institutionalisation. Order in fresh foods. Drink plain clean water. Empty your cupboards of all unnecessary (not recommend by an actual doctor at the time of consultation) vitamins, minerals, proteins, herbals, naturopathic, tonics, potions, and the rest.
Read the product information leaflets available for every prescription drug, and registered pharmacy products.
Treat yourself like a scholar and be in the know about side effects, adverse effects that are signs and symptoms of the human body not liking what is happening. THESE ARE NOT Reactions that the human body is meant to get used to. Off food toxins causes people to vomit. So when prescription drugs cause vomiting, it should be tolerated?!
Why?
For all the money it costs to ingest synthetic licit drugs, surely buying fresh foods, would work out less expensive, less costly in the longer term, and probably (50:50 better odds than psych. pharma) more effective and beneficial within the allocated 4 weeks to 6 weeks that it takes pharma drugs to begin to “work”.
Toss that coin again: one side says doctor visit and drugs, the other side says shop more wisely, cook (arggh who wants to shop, prepare, cook, serve, clean) cleanly, and not have to tolerate nausea, vomiting, weight loss, weight gain, constipation, headaches, feeling cold, feeling flushed, pins and needles, mental fog, mental slowing, feeling faint, palpitations, (read side effects, adverse effects on product information leaflet).
Always check in with your GP or a GP to check all your vital signs and to ensure that possible medical conditions are considered and investigated.
Report comment
Your description is perfect. The effects on human beings’ bodies and brains and minds.
Society has put the “experts” of psych. (psychiatrists, psychologists, GPs, doctors, researchers) at the top of the totem poles, from where they influence social policies, procedures, and justice systems.
Report comment